Tag: GLP-1 insurance

  • Medicare Open Enrollment 2027: A Checklist for Diabetes and GLP-1 Care

    A practical way to compare prescription coverage, pharmacies, and care access—without mistaking a low premium for a low yearly bill.

    Published: October 1, 2026 · Last updated: October 1, 2026

    Quick answer

    Medicare open enrollment 2027 is the fall 2026 opportunity to choose coverage for next year. The enrollment window runs October 15–December 7, 2026, with changes taking effect January 1, 2027. Start by reviewing your current plan’s changes, then compare your exact medicines and pharmacies—not just the monthly premium. Medicare’s enrollment dates and options.

    If you take a GLP-1, establish whether your prescription goes through ordinary Part D coverage or the separate Medicare GLP-1 Bridge. Those are different payment routes. A promising price in a search result does not confirm that your prescription qualifies. CMS Bridge guidance.

    The essentials before you compare

    • Use the 2027 plan documents, even if the plan name looks unchanged.
    • Compare yearly prescription costs and monthly cash flow separately.
    • Check the exact medicine, strength, formulation, and quantity.
    • Resolve coverage restrictions before treating an estimate as dependable.
    • Keep a written record of the plan, pharmacy, documents, and answers you used.

    This is a coverage-planning guide, not a recommendation to switch plans or change treatment. Its purpose is to help you ask more precise questions before a decision.

    Why review your plan now?

    On September 28, CMS released its 2027 Medicare Advantage and prescription-drug market update. It projected relatively stable average standalone Part D premiums and highlighted new comparison features arriving in October. National averages, however, are not a quote for your ZIP code or medication list. Read the CMS 2027 announcement.

    Think of the comparison as checking a route before a long trip. The sign may look familiar while a turn has changed. A useful review asks: can I still obtain my prescribed treatment, from a workable pharmacy, with a budget I understand?

    Your plan’s Annual Notice of Change (ANOC) should arrive in September. It outlines changes taking effect in January. If you did not receive it, request it from your plan. Medicare’s explanation of the ANOC.

    Step 1: Make a medication list that a computer can actually price

    “Diabetes injection” is not specific enough. Before opening a comparison tool, put your prescription labels beside you. For each medicine, record:

    • The full name and whether the prescription specifies a brand.
    • The strength and formulation, such as a tablet, vial, or particular pen.
    • The prescribed quantity and refill interval.
    • The pharmacy you actually use, plus a realistic alternative.
    • Any current approval letter and its expiration date.

    Then check the list against your clinician’s current medication record. Do not include an old prescription you no longer take merely because it remains in a saved account. Equally, do not omit an expensive medicine because you fill it only occasionally.

    Medicare’s comparison tools can use your prescriptions to estimate monthly and yearly costs. The quality of that estimate depends on the information you enter. If a medicine or quantity cannot be entered correctly, write down the mismatch and ask the plan to resolve it.

    Step 2: Separate a formulary listing from permission to fill

    A formulary is a plan’s covered-drug list. Finding a drug there is important, but it is not the final coverage check.

    Plans may require prior authorization, step therapy, or quantity limits. In plain language, these can mean approval before payment, trying a specified alternative first, or a limit on the amount covered. Some drugs are covered only for particular medical conditions. Medicare’s drug-plan rules.

    For each important medicine, ask: “What must my prescriber submit for this exact prescription in 2027?” Also ask whether an existing approval remains valid after the plan or year changes. Do not assume either answer.

    If the answer is unclear, ask for the relevant coverage document or a written explanation. A customer-service conversation is useful preparation, but it does not replace a required coverage decision. For a current rejection, our GLP-1 denial and appeal guide explains how to organize the next questions.

    Step 3: Use a Medicare open enrollment 2027 comparison sheet

    Copy the following checklist into a note. Add one column for your current plan’s 2027 version and another for each alternative. Leave unresolved items marked “not confirmed” rather than treating a blank as a yes.

    A practical worksheet—not a coverage guarantee
    CheckWhat to recordQuestion to resolve
    Plan identityYear, full plan name, plan ID, service areaAm I reading the correct version?
    Prescription accessExact drug and formulation; restrictionsIs approval needed for my prescribed use?
    PharmacyLocation, network status, estimated costCan I reliably use this pharmacy?
    Annual budgetPremiums and estimated drug spendingWhat is included or missing?
    Early-year costsJanuary and February estimatesCan I manage the timing of payments?
    Care continuityClinicians, suppliers, current authorizationsWhat needs confirmation before switching?

    On a phone, swipe the table horizontally. This worksheet is our editorial planning aid; the plan’s documents and coverage decisions govern benefits.

    Step 4: Compare the annual bill, not just the premium

    Medicare lists a maximum Part D deductible of $700 for 2027 and a $2,400 annual out-of-pocket limit for covered Part D drugs. Some plans have a lower deductible or none. These figures are not a cap on all health spending, and a drug must be covered for the Part D protection to apply. Premiums are a separate expense. Medicare’s current drug-cost guidance.

    Consider this fictional arithmetic example, not a real plan quote. Plan A has a $10 monthly premium and $900 in estimated annual prescription spending: $1,020 together. Plan B has a $40 premium and $300 in prescription spending: $780 together. The higher-premium option is $240 cheaper on those two inputs.

    That does not make Plan B universally better. First verify that both estimates use the same drugs, quantities, and pharmacy assumptions. Also check what the displayed total already includes so you do not add a deductible twice. Keep medical expenses, uncovered items, and any separate program costs visible rather than hiding them inside one optimistic total.

    Step 5: Price a pharmacy you can realistically use

    Being in network and having preferred cost sharing are not always the same thing. Medicare explains that preferred in-network pharmacies may offer lower out-of-pocket prices than other network pharmacies. Out-of-network fills will often cost more. Medicare’s pharmacy guidance.

    Compare your usual pharmacy with at least one practical alternative. Then consider travel, opening hours, refill coordination, and delivery needs. A lower estimate is less useful if collecting the medication becomes difficult.

    Ask the pharmacy about the specific product and dispensing arrangements. Do not interpret a favorable insurance estimate as confirmation that the product will be in stock whenever you need it.

    Step 6: Keep ordinary Part D and the GLP-1 Bridge separate

    The Medicare GLP-1 Bridge currently runs through December 31, 2027. CMS says it operates outside normal Part D payment and coverage. Its $50 copayment does not count toward Part D true out-of-pocket spending, and the Part D deductible does not apply to Bridge prescriptions. CMS’s program explanation.

    This distinction matters when comparing plans. Do not add a Bridge payment to the Part D tracker and assume it helps you reach the annual drug limit. Equally, do not select a plan solely because you expect it to make you eligible for the Bridge.

    Eligibility depends on more than enrollment in drug coverage. Medicare’s guidance distinguishes the Bridge from treatment covered through Part D and lists specific clinical and product requirements. Ask your prescriber and Medicare which route applies to you. Check the official eligibility guidance.

    Our Medicare GLP-1 coverage guide provides additional background. For a current enrollment decision, use the live official documents linked here if older explanations differ.

    Step 7: Check care access before changing the coverage structure

    If you are considering Medicare Advantage, review the plan type and its provider-access rules—not just the prescription section. Medicare’s comparison of Advantage plan types explains why those rules differ.

    Make a short list of the people and services you need to keep: your usual clinician, diabetes specialist, hospital, and equipment supplier where relevant. Ask both the plan and the provider about the exact 2027 plan. “We take that insurer” is less precise than confirmation of the specific product.

    Moving to Original Medicare introduces another question: access to Medigap. The fall enrollment period is not an annual guarantee that you can buy any Medigap policy without underwriting. Federal protections are limited, and state rules can add rights. Check your position before leaving coverage you want to preserve. Medicare’s Medigap buying guidance.

    Step 8: Plan the first refill—not just enrollment day

    Before submitting an enrollment choice, make a transition note: intended start date, next refill date, unresolved approval questions, and whom to contact if the pharmacy cannot process the prescription. Keep the enrollment confirmation and your comparison documents together.

    Some people may receive a one-time transition supply when new drug coverage starts, but this is not a promise of indefinite coverage. Ask the plan how its transition policy applies to your prescription. Medicare’s transition-fill explanation.

    If payment timing is the obstacle, the Medicare Prescription Payment Plan can spread eligible out-of-pocket drug costs across the calendar year. It changes when you pay, not the total price. Ask separately about financial assistance rather than treating payment smoothing as a discount.

    A call script you can save

    “I am comparing your 2027 plan, not my current-year benefits. Please help me confirm this exact prescription, its restrictions, and the cost at my pharmacy. Does an existing approval carry over? Where can I find the written rule? If I switch, what should my prescriber do before my first refill?”

    Write the date, reference number, and unresolved questions below the answer. If two representatives disagree, request clarification against the same written plan document. You do not need to make an immediate choice just because someone answered the phone.

    Frequently asked questions

    Can I make my annual enrollment change on October 1?

    October 1 is a preparation and comparison date. The regular fall election window begins October 15. Other enrollment rights may apply in specific circumstances; do not assume this general calendar describes every situation. Check Medicare’s enrollment guidance.

    Must I switch plans every year?

    No. CMS says people keeping their existing coverage generally do not need to re-enroll. However, reviewing the next year’s terms is still useful. Check any notice that your plan is ending or changing. CMS’s annual review advice.

    Who can help without choosing a plan for me?

    Your State Health Insurance Assistance Program (SHIP) provides local, unbiased Medicare counseling. Bring your comparison sheet and unresolved questions. Medicare also offers help at 1-800-MEDICARE.

    Should I change medication to match a cheaper plan?

    Do not change treatment yourself. Take the coverage issue to your prescriber. This checklist helps compare access to care; it does not decide which medicine is clinically appropriate.

    Bottom line

    A useful Medicare open enrollment 2027 review ends with fewer unknowns—not necessarily a new plan. Confirm your medicines, compare realistic costs, check care access, and prepare for the first refill. A small file of verified answers is more useful than a folder of attractive advertisements.

    Sources and further reading

    This practical guide uses official coverage information checked October 1, 2026. It is not a systematic clinical review or a personalized plan recommendation. Prices, benefits, and program rules may change; verify the relevant plan and year before enrolling.

    Written and edited by: Denny Jaeyong Choi (JD), INSEAD MBA

    Prepared with AI assistance. This procedural coverage guide does not claim individual medical or scientific review.

    Medical and coverage information notice: General education only; not personal diagnosis, treatment, legal advice, or a guarantee of insurance payment. Discuss medication decisions with your clinician and confirm coverage with Medicare or your plan.

  • GLP-1 Prior Authorization Denied? How to Appeal in 2026

    GLP-1 Prior Authorization Denied? How to Appeal in 2026

    If your GLP-1 prior authorization was denied, the next step is not always “write an appeal.” First identify whether the problem is missing information, a formulary rule, step therapy, medical-necessity criteria, a benefit exclusion, or the wrong coverage pathway.
    Written and edited by Denny Jaeyong Choi (JD), INSEAD MBA
    Published September 12, 2026 · Last updated September 12, 2026

    GLP-1 prior authorization denial: quick answer

    If you received a GLP-1 prior-authorization denial, get the written denial and its exact reason before doing anything else. A missing chart note may be fixed by resubmission, while a medical-necessity denial may need an internal appeal supported by your prescriber. A nonformulary drug may require a formulary exception. A plan-wide exclusion may be much harder to overturn because medical evidence does not automatically create a benefit the plan excludes.

    Deadlines depend on the plan. HealthCare.gov says many commercial-plan internal appeals must be filed within 180 days of the denial notice, while a federal external-review request generally must be filed within four months of the final denial. Employer plans, Medicare Part D, Medicaid, and the temporary Medicare GLP-1 Bridge follow different procedures. Start with the instructions printed on your own denial notice.

    The practical rule: denial reason first, evidence second, correct pathway third. Do not send the same generic letter to every plan.

    GLP-1 prior authorization appeal: key takeaways

    • Ask for the denial in writing. Record the date, denial code, policy cited, deadline, and appeal address or portal.
    • Separate a fixable submission problem from a coverage decision. A missing form is different from a benefit exclusion.
    • Build the appeal around the plan’s actual criteria. More pages do not make a stronger appeal if they do not answer the stated reason.
    • Keep the product and indication precise. Plans evaluate the exact brand, formulation, dose, diagnosis, and requested use.
    • Use the correct system. Commercial plans, self-funded employer plans, Medicare Part D, Medicaid, and the Medicare GLP-1 Bridge do not share one appeal process.
    • Request expedited review only when medically appropriate. The treating clinician should explain why the standard timeline could seriously jeopardize health or the ability to regain maximum function.
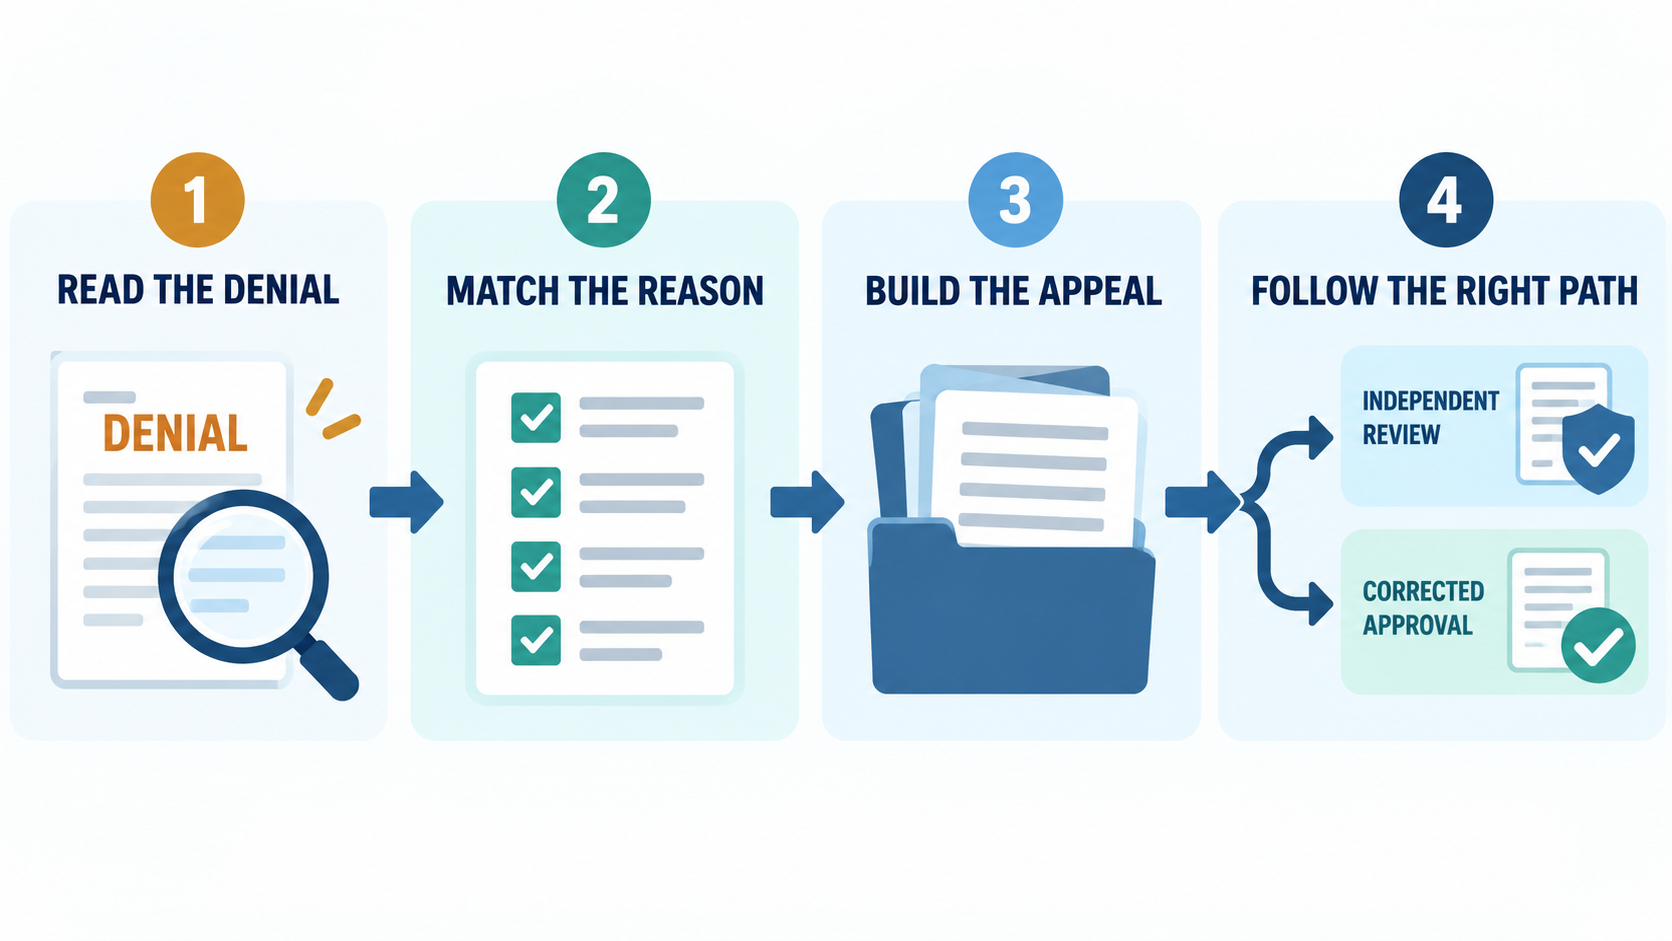
    GLP-1 prior authorization denial appeal pathway: read the denial, match the reason, build an appeal, and follow the correct review path
    A GLP-1 prior-authorization denial is the starting point: identify the reason before choosing an internal appeal, external review, or correction.

    GLP-1 prior authorization: read the denial first

    A pharmacy message such as “PA required,” “not covered,” or “refill too soon” is useful, but it may not be the plan’s final written decision. Ask the pharmacy for the rejection message and ask the plan or pharmacy-benefit manager for the formal notice. The notice should identify what was denied, why, what evidence was considered, and how to challenge the decision.

    For many private plans, HealthCare.gov’s internal-appeal guidance says the insurer must explain a denial in writing. For job-based plans governed by ERISA, the U.S. Department of Labor says participants can request relevant claim documents and records without charge. These documents help you see whether the decision turned on the benefit design, the formulary, a clinical rule, or incomplete information.

    Write down these eight facts

    1. Exact drug name, formulation, strength, and quantity
    2. Diagnosis or indication submitted by the prescriber
    3. Date the request and denial were issued
    4. Denial code and reason quoted word for word
    5. Policy, formulary, or prior-authorization criteria cited
    6. Internal-appeal deadline and submission method
    7. Whether an expedited review is available
    8. Reference numbers and the names and dates of phone conversations

    GLP-1 prior authorization: match the denial reason

    Common GLP-1 denial reasons and the most useful next step
    Denial reason What it usually means Best first response
    Missing information The form, chart note, diagnosis, laboratory result, treatment history, or signature was incomplete. Correct the missing item and resubmit; confirm receipt.
    Benefit exclusion The plan may exclude drugs used for weight management as a category. Verify that the exclusion applies to the submitted indication and ask whether any exception exists.
    Nonformulary drug The requested product is not on the current covered-drug list. Request a formulary exception and address why covered alternatives are unsuitable.
    Step therapy The plan requires one or more preferred treatments first. Document completed steps or request an exception based on accurate clinical facts.
    Criteria not met The request did not satisfy the plan’s BMI, diagnosis, comorbidity, duration, or program rules. Compare the record with each criterion and correct factual errors; do not alter facts to fit a policy.
    Renewal denied The plan may require documented response, adherence, follow-up, or a current authorization. Submit the requested follow-up data and explain any clinically relevant interruption.

    A benefit exclusion deserves special caution. A prescriber’s statement that a drug is medically necessary can be important, but it does not automatically override a contract that excludes a benefit. The useful question is whether the exclusion was applied correctly to the exact indication. For example, the same drug family may be evaluated differently when used for weight management versus an FDA-approved condition that the plan covers. Our 2026 weight-loss medication coverage guide explains how benefit exclusions, formularies, indications, and utilization rules differ.

    GLP-1 prior authorization: choose the right appeal pathway

    Commercial or Marketplace plan

    HealthCare.gov describes two levels: an internal appeal to the insurer and, for qualifying denials, an independent external review. Its current guidance says an internal appeal generally must be filed within 180 days after the denial notice. A standard internal decision is generally due within 30 days for care not yet received and 60 days for services already received. Read the plan notice because the precise process and any additional levels can vary.

    If the final internal decision still denies a matter involving medical judgment, an external review may be available. HealthCare.gov’s external-review page says the request generally must be filed within four months; standard reviews are decided no later than 45 days and expedited reviews no later than 72 hours. The final denial should tell you whether the state or the federal process applies.

    Temporary 2026 notice: As checked September 12, HealthCare.gov says some people whose federal external-review deadline fell between July 1 and August 3, 2026 may have an extension until October 2, 2026. It may apply in Alabama, Florida, Georgia, Texas, Wisconsin, certain territories, and some state or local government plans. Confirm directly with the plan or federal reviewer rather than assuming the extension applies.

    Self-funded employer plan

    Many employer plans are self-funded and governed by federal ERISA rules even when an insurance company administers the claims. Read the Summary Plan Description and denial notice. The Department of Labor’s benefits-claim guide says a participant has at least 180 days to appeal and can request documents relevant to the claim. The notice should explain the plan’s external-review rights when applicable. The Employee Benefits Security Administration can answer questions about ERISA rights, but it does not replace the plan’s filing deadline.

    Medicare Part D

    For a drug that may be covered under ordinary Part D, begin with a coverage determination or formulary exception. CMS says an enrollee, prescriber, or representative may request a standard or expedited determination. A standard request for benefits is generally decided within 72 hours and an expedited request within 24 hours; for an exception, the clock begins when the plan receives the prescriber’s supporting statement.

    If the Part D determination is unfavorable, CMS calls the first appeal a redetermination. The current CMS redetermination guidance gives 65 calendar days from the notice date to file. The plan generally has seven calendar days for a standard redetermination and 72 hours for an expedited one. Later levels can involve an Independent Review Entity, so follow the instructions in each decision.

    Medicare GLP-1 Bridge

    The temporary Medicare GLP-1 Bridge is different from ordinary Part D. CMS states that the Bridge has no formal appeal process. If the prior authorization contained incorrect, incomplete, updated, or additional information, the prescriber may submit it again. The pharmacy claim must establish Bridge eligibility before the prescriber sends the authorization; submitting in the wrong order can produce a “patient not found” error. See the CMS provider FAQ and our Medicare GLP-1 Bridge guide.

    Medicaid

    Medicaid drug coverage and prior-authorization rules are state-specific. Use the deadline and appeal or fair-hearing instructions in the state notice. CMS explains that states must provide an opportunity for a fair hearing when benefits or services are denied, reduced, suspended, or terminated, but filing methods and timelines vary. See the CMS Medicaid fair-hearing factsheet and your state Medicaid agency’s current rules.

    Step 4: build a focused GLP-1 prior authorization appeal packet

    A strong packet answers the denial rather than retelling the entire medical history. Ask the prescribing office which parts it will submit and which parts you must submit. Keep copies of everything.

    • The written denial or Explanation of Benefits
    • The current formulary entry, prior-authorization criteria, or policy cited
    • The original authorization request and proof of submission
    • A concise prescriber letter addressing each disputed criterion
    • Relevant chart notes, diagnosis information, measurements, laboratory results, or treatment history
    • Accurate records of covered alternatives tried, contraindicated, ineffective, or poorly tolerated
    • The exact requested product, formulation, strength, quantity, and intended indication
    • An authorized-representative form if the clinician or another person will file for you
    • A dated index listing every attachment

    Do not add unrelated records “just in case.” Extra pages can obscure the one missing fact. If weight history or complications are central to the policy, our complete obesity evaluation guide can help you understand the kinds of clinical context a careful evaluation may document. It is not a checklist for gaming coverage criteria.

    A practical GLP-1 appeal letter template

    Subject: Request for internal appeal of GLP-1 coverage denial

    Member: [name]
    Member ID: [ID]
    Request or claim number: [number]
    Drug: [exact brand, formulation, strength, and quantity]
    Denial date: [date]

    I am requesting a full review of the denial identified above. The denial notice states: “[quote the reason exactly].”

    The enclosed information addresses that reason as follows:

    1. [Plan criterion or disputed fact]
    2. [Accurate supporting information and attachment]
    3. [Why the requested exception applies, if relevant]

    Please reconsider the request and provide the decision in writing. If additional information is required, please identify the missing item and the deadline. Please also provide the policy, clinical criteria, and claim records relied on for the decision if they have not already been supplied.

    Attachments: [numbered list]

    Adapt the letter to the plan. Medicare uses its own determination and appeal terminology; Medicaid notices may require a state form; a missing-information denial may be faster to correct and resubmit than to package as a formal appeal.

    When should a GLP-1 prior authorization appeal be expedited?

    Do not label a case urgent simply to move it faster. Ask the treating clinician whether waiting through the standard process could seriously jeopardize life, health, or the ability to attain, maintain, or regain maximum function. When that standard is met, the clinician should state the reason clearly and use the plan’s expedited process.

    HealthCare.gov says a person in an urgent situation may request an external review while the internal appeal is still pending. Medicare Part D also permits expedited coverage determinations and redeterminations when the regulatory standard is met. If symptoms themselves require urgent medical attention, contact appropriate medical services; an insurance appeal is not emergency care.

    What to do after you submit a GLP-1 prior authorization appeal

    1. Confirm receipt. Ask for the date, time, reference number, and number of pages received.
    2. Check whether the packet is complete. Confirm that the prescriber’s statement and attachments are visible in the file.
    3. Calendar the decision deadline. Use the plan’s written timeframe, not an estimate from a general article.
    4. Request the decision in writing. A phone approval is helpful, but the written outcome controls the next step.
    5. If denied again, read the new reason. The next notice should explain external review, further Medicare levels, a fair hearing, or other rights.
    6. Keep cash payment separate. Paying out of pocket does not guarantee later reimbursement or deductible credit. Our 2026 self-pay comparison explains current manufacturer channels, and our HSA and FSA guide explains when unreimbursed expenses may qualify.

    Frequently asked questions

    Does a GLP-1 prior-authorization denial mean the drug can never be covered?

    No. Some denials are caused by missing information or an unmet administrative step and can be corrected. Others involve medical-necessity criteria or a formulary exception that can be appealed. A categorical benefit exclusion may be harder to change. The written reason tells you which situation you have.

    Should I appeal or ask the office to resubmit?

    If the notice identifies missing or incorrect information, a corrected resubmission may be the direct response. If the plan has made an adverse coverage decision after reviewing a complete request, follow the formal appeal instructions. Ask the plan to state which process it expects.

    Can my doctor appeal for me?

    Often yes, but the plan may require an authorized-representative form. The prescriber may also be needed for the clinical statement or an expedited request. Confirm responsibilities so the same appeal is not lost between the patient, clinic, pharmacy, and plan.

    Will a letter of medical necessity guarantee approval?

    No. A focused letter can address medical-necessity or exception criteria, but it cannot guarantee coverage and may not overcome a plan-wide exclusion. The letter should use accurate clinical facts and respond to the policy cited in the denial.

    Can I appeal a step-therapy requirement?

    Many plans provide an exception process. The prescriber should explain, when accurate, which required alternatives were tried and what happened, or why a covered alternative is contraindicated or expected to be less effective. Requirements vary by plan and state.

    What if the Medicare GLP-1 Bridge denies the request?

    CMS says the Bridge itself has no formal appeal process. The prescriber can resubmit when the original request contained incorrect information or when updated or additional information is available. Do not confuse this with ordinary Part D appeal rights for a Part D-coverable indication.

    Does an external reviewer have to follow the plan’s decision?

    An external reviewer independently evaluates qualifying denials. HealthCare.gov states that when the reviewer overturns the insurer’s decision, the insurer must accept that outcome. Eligibility for external review depends on the denial and the plan, so use the instructions in the final internal denial.

    Bottom line: your GLP-1 prior authorization appeal

    When a GLP-1 prior authorization is denied, speed comes from precision. Get the written reason, identify the plan type, match the response to the exact denial, and submit only the evidence that answers it. A correction, formulary exception, internal appeal, external review, Medicare redetermination, Medicaid fair hearing, and Medicare GLP-1 Bridge resubmission are not interchangeable.

    Sources and further reading

    Written and edited by: Denny Jaeyong Choi (JD), INSEAD MBA

    This article was prepared with AI-assisted research and drafting and checked against the cited U.S. government sources on September 12, 2026. It provides general educational information, not individualized medical, legal, tax, or insurance advice. Coverage policies, formularies, deadlines, and government programs can change. Verify the current notice, plan documents, and official instructions before acting.

  • Does Insurance Cover Weight Loss Medication in 2026? A Practical GLP-1 Guide

    Does Insurance Cover Weight Loss Medication in 2026? A Practical GLP-1 Guide

    Quick answer: Weight loss medication coverage varies by plan. Insurance sometimes covers prescription treatment, but payment depends on the exact drug and formulation, the diagnosis being treated, and whether you complete requirements such as prior authorization. A prescription by itself does not guarantee payment.

    To understand weight loss medication coverage, the fastest way to get a reliable answer is not to ask, “Do you cover GLP-1 drugs?” Ask whether your plan covers the exact product for your specific FDA-approved indication, then request the written coverage policy and prior-authorization form. This guide explains how to do that, what evidence your clinician may need, and how to respond if the claim is denied.

    The answer depends on four separate questions

    1. Does your plan include anti-obesity medications? Some plans exclude the entire benefit category, even when they cover other prescription drugs.
    2. Is the exact drug on the formulary? Coverage may differ by brand, dose, device, and formulation.
    3. Is it being prescribed for a covered indication? The same active ingredient can be sold under different brand names with different FDA-approved uses.
    4. Have you met the utilization rules? Prior authorization, step therapy, quantity limits, network-pharmacy rules, and renewal criteria can all affect payment.

    Why the name on the prescription matters

    “Semaglutide” or “tirzepatide” is not enough information for an insurance check. Insurers adjudicate the specific product and indication. For example, the FDA labels Wegovy for chronic weight management and certain additional indications, while the Ozempic label is centered on type 2 diabetes and related cardiovascular and kidney-risk reduction. Similarly, Zepbound is approved for chronic weight management, whereas Mounjaro is labeled for type 2 diabetes.

    ProductActive ingredientSelected FDA-approved use relevant to coveragePractical insurance implication
    WegovySemaglutideChronic weight management; cardiovascular-risk reduction in qualifying adults; additional labeled usesMay be evaluated under an obesity benefit or another covered indication, depending on the plan
    ZepboundTirzepatideChronic weight management; moderate-to-severe obstructive sleep apnea in adults with obesityAsk which indication and clinical criteria the plan uses
    OzempicSemaglutideType 2 diabetes and related labeled risk-reduction usesUse solely for weight loss may be treated as off-label and denied
    MounjaroTirzepatideType 2 diabetesUse solely for weight loss may be treated as off-label and denied
    FDA labels evolve. Confirm the current label and your plan policy rather than assuming that drugs with the same ingredient are interchangeable.

    Zepbound also has an FDA-approved indication for moderate-to-severe obstructive sleep apnea in adults with obesity. That does not guarantee coverage, but it can change which policy and documentation apply. Your clinician should identify the medically appropriate, labeled indication rather than trying to “game” the claim.

    Weight loss medication coverage by insurance type

    Employer-sponsored and other commercial plans

    Two people with the same insurance company can have different benefits because employers often choose different prescription designs. One plan may cover anti-obesity drugs with prior authorization; another may exclude them. Start with the Summary Plan Description or pharmacy benefit materials, then call the number on the prescription card. For employer plans, the U.S. Department of Labor recommends consulting the plan documents and following the plan’s claims and appeal procedures.

    Marketplace and individual plans

    Review the plan’s drug formulary and Summary of Benefits and Coverage. HealthCare.gov advises members to check whether a medicine is covered, what it costs, and whether an exception process is available. Marketplace plans must provide a way to appeal many adverse benefit decisions, but that process cannot necessarily override a clearly written benefit exclusion.

    Medicaid

    Medicaid prescription coverage is state-specific. Check your state Medicaid agency’s current preferred drug list and prior-authorization criteria. Do not assume that a policy in a neighboring state applies to you. The federal State Prescription Drug Resources page is a useful starting point.

    Medicare weight loss medication coverage in 2026

    As of September 4, 2026: the CMS Medicare GLP-1 Bridge is a temporary nationwide demonstration running from July 1, 2026 through December 31, 2027 for eligible Medicare Part D beneficiaries. CMS states that eligible participants pay a $50 monthly copay and must obtain prior authorization.

    Current Bridge products listed by CMS include certain formulations of Foundayo, Wegovy, and Zepbound; the list may change. Clinical eligibility includes adults with obesity or overweight who meet specific BMI and comorbidity criteria. People using a GLP-1 for another coverable Part D indication—such as type 2 diabetes, qualifying obstructive sleep apnea, or certain liver-disease indications—may need to seek coverage through their Part D plan rather than the Bridge.

    Check the current Medicare consumer guidance and CMS Bridge criteria before acting. These details are time-sensitive.

    How to check weight loss medication coverage: six steps

    1. Collect the exact prescription details

    • Brand name and active ingredient
    • Formulation and strength
    • Diagnosis or FDA-approved indication being treated
    • Prescriber’s name and contact information

    2. Search the current formulary

    Use the formulary for the current plan year—not an old PDF found through a general web search. Search for the brand name and review the notes for tier, prior authorization, step therapy, quantity limits, age limits, and specialty-pharmacy requirements. If the drug is absent, look for the plan’s formulary-exception process.

    3. Call the pharmacy-benefit number

    “I am checking coverage for [exact drug, formulation, and strength] for [diagnosis/indication]. Is anti-obesity medication included or excluded under my plan? Is this product on the current formulary? What tier is it, and does it require prior authorization, step therapy, quantity limits, or a specific pharmacy? Please send me the written policy and prior-authorization form, and give me a reference number for this call.”

    Also ask for your expected cost after the deductible, whether coinsurance is based on the negotiated price, and what renewal criteria apply. Record the date, representative’s name, and call reference number.

    4. Read the clinical criteria before the appointment

    Requirements vary, but policies may ask for a documented BMI, qualifying weight-related conditions, previous treatment attempts, participation in lifestyle modification, or reasons that preferred alternatives are inappropriate. These are plan rules, not universal medical standards. For context on cardiometabolic risk documentation, see our guide to the five metabolic syndrome criteria.

    5. Give your clinician the actual form

    Do not rely on a generic note saying “medically necessary.” A strong submission answers each question in the plan’s policy and may include:

    • Baseline and current weight, height, and BMI
    • Relevant diagnoses and objective clinical history
    • The FDA-approved indication being treated
    • Previous therapies, outcomes, adverse effects, or contraindications when the policy asks for them
    • Why a formulary alternative is expected to be less effective or unsafe, when applicable
    • A monitoring and follow-up plan

    6. Confirm approval before filling the prescription

    Ask for the authorization number, start and end dates, approved dose or quantity, required pharmacy, and renewal criteria. Approval does not always mean a low copay; verify your actual out-of-pocket amount before the pharmacy dispenses the medicine.

    Steps for checking coverage, prior authorization, and appealing a weight-loss medication denial
    A practical path from formulary check to prior authorization and appeal.

    If weight loss medication coverage is denied

    Denial reasonWhat it usually meansUseful next step
    Benefit exclusionThe plan excludes anti-obesity drugs as a categoryConfirm the exact exclusion in writing. An appeal may not overcome plan design; ask an employer benefits team about future coverage options.
    Non-formulary drugThe product is not on the covered listAsk about preferred alternatives and whether a formulary exception is available.
    Incomplete prior authorizationRequired fields or records were missingRequest the denial details and resubmit a complete packet promptly.
    Step therapy not completedThe plan requires a preferred treatment firstDocument the trial, failure, adverse effect, or clinical reason the required step is inappropriate.
    Indication not coveredThe diagnosis or use does not meet the policyVerify coding and the labeled indication; discuss a covered, medically appropriate alternative with the clinician.
    Renewal criteria not metThe plan requires a specified response or follow-upSubmit objective progress data, or discuss whether continuing treatment is clinically appropriate.

    How to appeal a denial

    1. Get the denial in writing. You need the reason, policy language, clinical criteria, appeal deadline, and submission route. Do not rely only on what the pharmacy screen says.

    2. Match the response to the reason. Ask the prescriber to address the specific missing criterion and attach relevant records. For a non-formulary request, explain why covered alternatives would be less effective, have caused adverse effects, or are contraindicated when that is medically accurate.

    3. File on time and keep a complete copy. HealthCare.gov states that an internal appeal generally must be filed within 180 days of receiving a denial. Include the denial or Explanation of Benefits, the appeal request, supporting clinician letters, records, and a log of calls. Your plan documents control the actual deadline.

    4. Request external review if eligible. If an internal appeal remains denied, an independent external review may be available. HealthCare.gov says the request is generally due within four months of the final denial; urgent cases may qualify for an expedited process.

    Medicare Part D exception: CMS allows requests for a non-formulary drug or for waiver of certain utilization rules. A prescriber’s supporting statement is important. CMS lists a standard decision timeframe of 72 hours, or 24 hours for an expedited request, after the supporting statement is received.

    Medicare GLP-1 Bridge exception: CMS says there is no formal appeal process for a Bridge prior-authorization denial. The provider may resubmit corrected or additional information, so obtain the precise reason and respond to it quickly.

    What to do if the drug is not covered

    • Ask about covered alternatives. The best alternative depends on your medical history, other medications, contraindications, and treatment goals.
    • Compare total cost, not only the coupon headline. Check the in-network pharmacy price, deductible, coinsurance, cash price, follow-up visits, and supplies.
    • Verify manufacturer program rules directly. Eligibility and terms can change, and government-insurance restrictions often apply.
    • Revisit employer benefits during enrollment. If the issue is a categorical exclusion, the benefits team—not the pharmacy—may be the relevant decision-maker.
    • Be cautious with compounded products. The FDA warns that unapproved compounded semaglutide and tirzepatide are not reviewed for safety, effectiveness, or quality in the same way as approved drugs. Use a state-licensed pharmacy and consider compounding only when a clinician determines that an approved product cannot meet the patient’s medical need.

    Frequently asked questions

    Does a prescription guarantee insurance coverage?

    No. A prescription indicates that a clinician ordered the drug; it does not establish that the plan includes the benefit, lists the product, or considers the patient eligible under its policy.

    Does insurance cover Ozempic for weight loss?

    Many plans evaluate Ozempic under its FDA-approved type 2 diabetes indications. Use solely for weight loss may be considered off-label and denied. Coverage is plan-specific, so check the exact formulary and policy. Wegovy contains semaglutide but has different labeled indications; it is not automatically covered either.

    Can my employer add weight-loss medication coverage?

    Potentially. For self-funded or employer-selected benefit designs, the employer or benefits consultant may influence which categories are included. Ask the benefits team whether the exclusion is an employer plan-design decision and whether it will be reviewed for the next plan year.

    Does Medicare cover weight-loss medication in 2026?

    Some eligible Part D beneficiaries can access selected products through the temporary Medicare GLP-1 Bridge beginning July 1, 2026, subject to prior authorization and clinical criteria. Other FDA-approved indications may be covered through the regular Part D benefit. Verify current CMS rules because the demonstration and product list are time-limited.

    How long does prior authorization take?

    It varies by plan and by whether the request is standard or urgent. Ask the plan when its review clock begins and what makes a submission complete. Do not confuse commercial-plan timelines with Medicare Part D exception timelines.

    Bottom line

    Weight loss medication coverage becomes easier to verify when the question is specific. The most useful question is not “Does insurance cover weight-loss drugs?” It is: “Does my current plan cover this exact product, for this diagnosis, under these clinical criteria, at this pharmacy, and at what out-of-pocket cost?” Get the answer in writing, give the correct policy to the prescriber, and treat a denial as a document with a specific reason—not as the end of the process.


    Sources and further reading

    Written and edited by: Denny Jaeyong Choi (JD), INSEAD MBA
    Last updated: September 7, 2026

    Medical information notice: This article provides general educational information and does not replace individualized medical advice, diagnosis, or treatment. Coverage rules change and your plan documents control. Discuss treatment decisions with a qualified clinician and verify benefits directly with your insurer.