
Quick answer: Weight loss medication coverage varies by plan. Insurance sometimes covers prescription treatment, but payment depends on the exact drug and formulation, the diagnosis being treated, and whether you complete requirements such as prior authorization. A prescription by itself does not guarantee payment.
To understand weight loss medication coverage, the fastest way to get a reliable answer is not to ask, “Do you cover GLP-1 drugs?” Ask whether your plan covers the exact product for your specific FDA-approved indication, then request the written coverage policy and prior-authorization form. This guide explains how to do that, what evidence your clinician may need, and how to respond if the claim is denied.
The answer depends on four separate questions
- Does your plan include anti-obesity medications? Some plans exclude the entire benefit category, even when they cover other prescription drugs.
- Is the exact drug on the formulary? Coverage may differ by brand, dose, device, and formulation.
- Is it being prescribed for a covered indication? The same active ingredient can be sold under different brand names with different FDA-approved uses.
- Have you met the utilization rules? Prior authorization, step therapy, quantity limits, network-pharmacy rules, and renewal criteria can all affect payment.
Why the name on the prescription matters
“Semaglutide” or “tirzepatide” is not enough information for an insurance check. Insurers adjudicate the specific product and indication. For example, the FDA labels Wegovy for chronic weight management and certain additional indications, while the Ozempic label is centered on type 2 diabetes and related cardiovascular and kidney-risk reduction. Similarly, Zepbound is approved for chronic weight management, whereas Mounjaro is labeled for type 2 diabetes.
| Product | Active ingredient | Selected FDA-approved use relevant to coverage | Practical insurance implication |
|---|---|---|---|
| Wegovy | Semaglutide | Chronic weight management; cardiovascular-risk reduction in qualifying adults; additional labeled uses | May be evaluated under an obesity benefit or another covered indication, depending on the plan |
| Zepbound | Tirzepatide | Chronic weight management; moderate-to-severe obstructive sleep apnea in adults with obesity | Ask which indication and clinical criteria the plan uses |
| Ozempic | Semaglutide | Type 2 diabetes and related labeled risk-reduction uses | Use solely for weight loss may be treated as off-label and denied |
| Mounjaro | Tirzepatide | Type 2 diabetes | Use solely for weight loss may be treated as off-label and denied |
Zepbound also has an FDA-approved indication for moderate-to-severe obstructive sleep apnea in adults with obesity. That does not guarantee coverage, but it can change which policy and documentation apply. Your clinician should identify the medically appropriate, labeled indication rather than trying to “game” the claim.
Weight loss medication coverage by insurance type
Employer-sponsored and other commercial plans
Two people with the same insurance company can have different benefits because employers often choose different prescription designs. One plan may cover anti-obesity drugs with prior authorization; another may exclude them. Start with the Summary Plan Description or pharmacy benefit materials, then call the number on the prescription card. For employer plans, the U.S. Department of Labor recommends consulting the plan documents and following the plan’s claims and appeal procedures.
Marketplace and individual plans
Review the plan’s drug formulary and Summary of Benefits and Coverage. HealthCare.gov advises members to check whether a medicine is covered, what it costs, and whether an exception process is available. Marketplace plans must provide a way to appeal many adverse benefit decisions, but that process cannot necessarily override a clearly written benefit exclusion.
Medicaid
Medicaid prescription coverage is state-specific. Check your state Medicaid agency’s current preferred drug list and prior-authorization criteria. Do not assume that a policy in a neighboring state applies to you. The federal State Prescription Drug Resources page is a useful starting point.
Medicare weight loss medication coverage in 2026
As of September 4, 2026: the CMS Medicare GLP-1 Bridge is a temporary nationwide demonstration running from July 1, 2026 through December 31, 2027 for eligible Medicare Part D beneficiaries. CMS states that eligible participants pay a $50 monthly copay and must obtain prior authorization.
Current Bridge products listed by CMS include certain formulations of Foundayo, Wegovy, and Zepbound; the list may change. Clinical eligibility includes adults with obesity or overweight who meet specific BMI and comorbidity criteria. People using a GLP-1 for another coverable Part D indication—such as type 2 diabetes, qualifying obstructive sleep apnea, or certain liver-disease indications—may need to seek coverage through their Part D plan rather than the Bridge.
Check the current Medicare consumer guidance and CMS Bridge criteria before acting. These details are time-sensitive.
How to check weight loss medication coverage: six steps
1. Collect the exact prescription details
- Brand name and active ingredient
- Formulation and strength
- Diagnosis or FDA-approved indication being treated
- Prescriber’s name and contact information
2. Search the current formulary
Use the formulary for the current plan year—not an old PDF found through a general web search. Search for the brand name and review the notes for tier, prior authorization, step therapy, quantity limits, age limits, and specialty-pharmacy requirements. If the drug is absent, look for the plan’s formulary-exception process.
3. Call the pharmacy-benefit number
“I am checking coverage for [exact drug, formulation, and strength] for [diagnosis/indication]. Is anti-obesity medication included or excluded under my plan? Is this product on the current formulary? What tier is it, and does it require prior authorization, step therapy, quantity limits, or a specific pharmacy? Please send me the written policy and prior-authorization form, and give me a reference number for this call.”
Also ask for your expected cost after the deductible, whether coinsurance is based on the negotiated price, and what renewal criteria apply. Record the date, representative’s name, and call reference number.
4. Read the clinical criteria before the appointment
Requirements vary, but policies may ask for a documented BMI, qualifying weight-related conditions, previous treatment attempts, participation in lifestyle modification, or reasons that preferred alternatives are inappropriate. These are plan rules, not universal medical standards. For context on cardiometabolic risk documentation, see our guide to the five metabolic syndrome criteria.
5. Give your clinician the actual form
Do not rely on a generic note saying “medically necessary.” A strong submission answers each question in the plan’s policy and may include:
- Baseline and current weight, height, and BMI
- Relevant diagnoses and objective clinical history
- The FDA-approved indication being treated
- Previous therapies, outcomes, adverse effects, or contraindications when the policy asks for them
- Why a formulary alternative is expected to be less effective or unsafe, when applicable
- A monitoring and follow-up plan
6. Confirm approval before filling the prescription
Ask for the authorization number, start and end dates, approved dose or quantity, required pharmacy, and renewal criteria. Approval does not always mean a low copay; verify your actual out-of-pocket amount before the pharmacy dispenses the medicine.
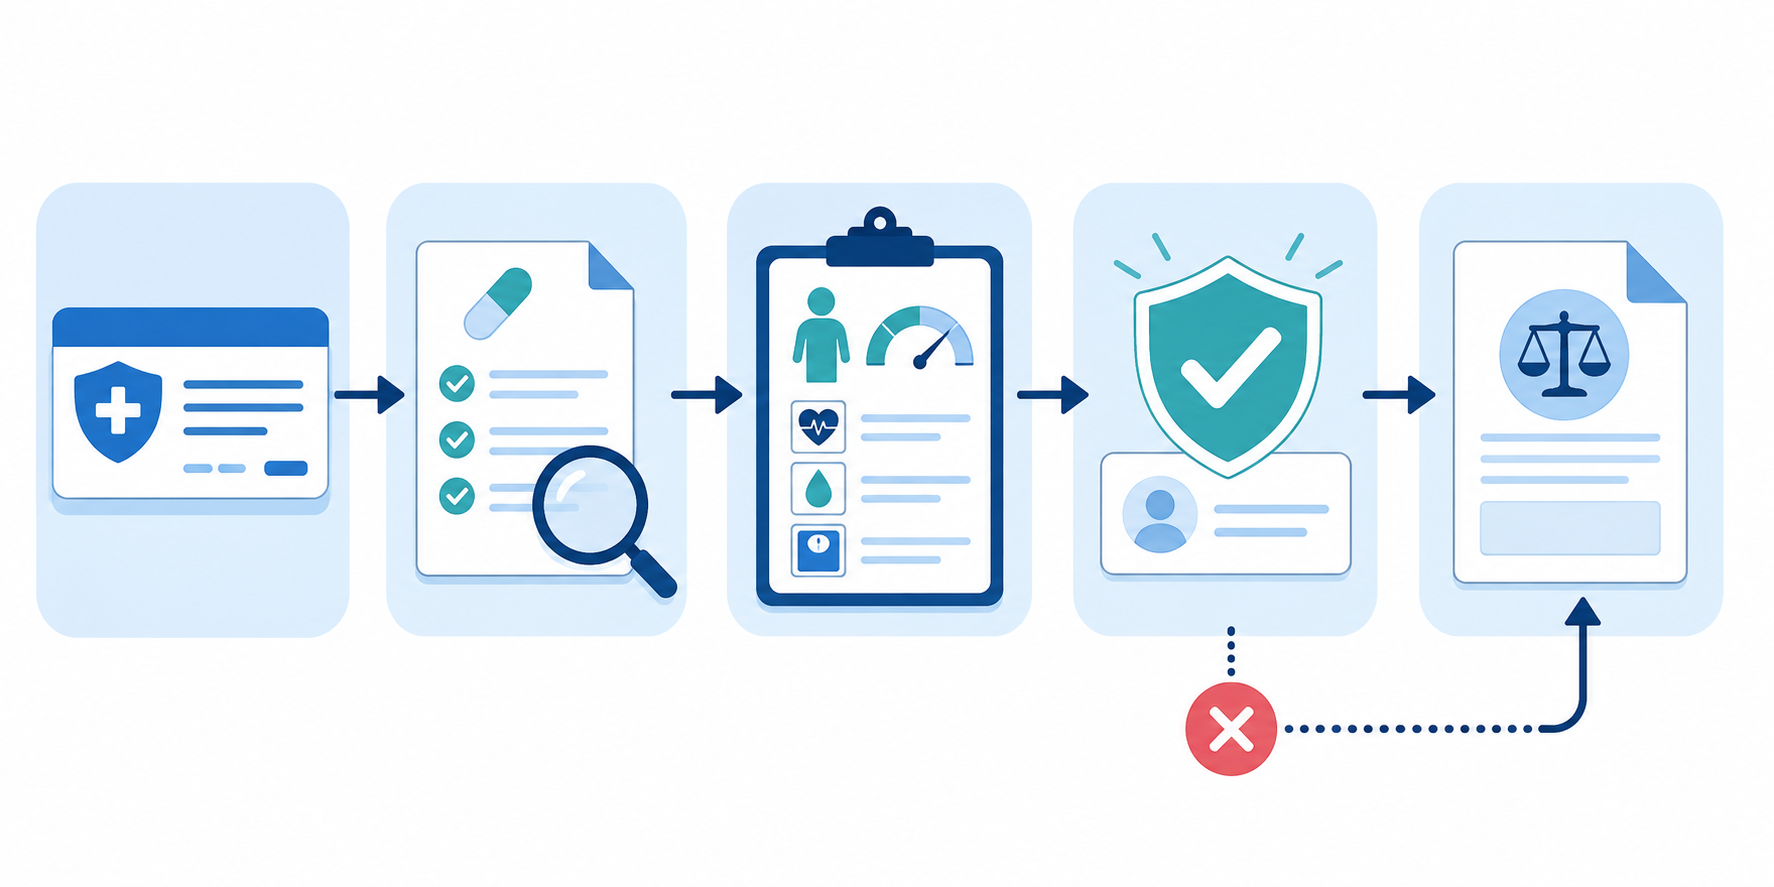
If weight loss medication coverage is denied
| Denial reason | What it usually means | Useful next step |
|---|---|---|
| Benefit exclusion | The plan excludes anti-obesity drugs as a category | Confirm the exact exclusion in writing. An appeal may not overcome plan design; ask an employer benefits team about future coverage options. |
| Non-formulary drug | The product is not on the covered list | Ask about preferred alternatives and whether a formulary exception is available. |
| Incomplete prior authorization | Required fields or records were missing | Request the denial details and resubmit a complete packet promptly. |
| Step therapy not completed | The plan requires a preferred treatment first | Document the trial, failure, adverse effect, or clinical reason the required step is inappropriate. |
| Indication not covered | The diagnosis or use does not meet the policy | Verify coding and the labeled indication; discuss a covered, medically appropriate alternative with the clinician. |
| Renewal criteria not met | The plan requires a specified response or follow-up | Submit objective progress data, or discuss whether continuing treatment is clinically appropriate. |
How to appeal a denial
1. Get the denial in writing. You need the reason, policy language, clinical criteria, appeal deadline, and submission route. Do not rely only on what the pharmacy screen says.
2. Match the response to the reason. Ask the prescriber to address the specific missing criterion and attach relevant records. For a non-formulary request, explain why covered alternatives would be less effective, have caused adverse effects, or are contraindicated when that is medically accurate.
3. File on time and keep a complete copy. HealthCare.gov states that an internal appeal generally must be filed within 180 days of receiving a denial. Include the denial or Explanation of Benefits, the appeal request, supporting clinician letters, records, and a log of calls. Your plan documents control the actual deadline.
4. Request external review if eligible. If an internal appeal remains denied, an independent external review may be available. HealthCare.gov says the request is generally due within four months of the final denial; urgent cases may qualify for an expedited process.
Medicare Part D exception: CMS allows requests for a non-formulary drug or for waiver of certain utilization rules. A prescriber’s supporting statement is important. CMS lists a standard decision timeframe of 72 hours, or 24 hours for an expedited request, after the supporting statement is received.
Medicare GLP-1 Bridge exception: CMS says there is no formal appeal process for a Bridge prior-authorization denial. The provider may resubmit corrected or additional information, so obtain the precise reason and respond to it quickly.
What to do if the drug is not covered
- Ask about covered alternatives. The best alternative depends on your medical history, other medications, contraindications, and treatment goals.
- Compare total cost, not only the coupon headline. Check the in-network pharmacy price, deductible, coinsurance, cash price, follow-up visits, and supplies.
- Verify manufacturer program rules directly. Eligibility and terms can change, and government-insurance restrictions often apply.
- Revisit employer benefits during enrollment. If the issue is a categorical exclusion, the benefits team—not the pharmacy—may be the relevant decision-maker.
- Be cautious with compounded products. The FDA warns that unapproved compounded semaglutide and tirzepatide are not reviewed for safety, effectiveness, or quality in the same way as approved drugs. Use a state-licensed pharmacy and consider compounding only when a clinician determines that an approved product cannot meet the patient’s medical need.
Frequently asked questions
Does a prescription guarantee insurance coverage?
No. A prescription indicates that a clinician ordered the drug; it does not establish that the plan includes the benefit, lists the product, or considers the patient eligible under its policy.
Does insurance cover Ozempic for weight loss?
Many plans evaluate Ozempic under its FDA-approved type 2 diabetes indications. Use solely for weight loss may be considered off-label and denied. Coverage is plan-specific, so check the exact formulary and policy. Wegovy contains semaglutide but has different labeled indications; it is not automatically covered either.
Can my employer add weight-loss medication coverage?
Potentially. For self-funded or employer-selected benefit designs, the employer or benefits consultant may influence which categories are included. Ask the benefits team whether the exclusion is an employer plan-design decision and whether it will be reviewed for the next plan year.
Does Medicare cover weight-loss medication in 2026?
Some eligible Part D beneficiaries can access selected products through the temporary Medicare GLP-1 Bridge beginning July 1, 2026, subject to prior authorization and clinical criteria. Other FDA-approved indications may be covered through the regular Part D benefit. Verify current CMS rules because the demonstration and product list are time-limited.
How long does prior authorization take?
It varies by plan and by whether the request is standard or urgent. Ask the plan when its review clock begins and what makes a submission complete. Do not confuse commercial-plan timelines with Medicare Part D exception timelines.
Bottom line
Weight loss medication coverage becomes easier to verify when the question is specific. The most useful question is not “Does insurance cover weight-loss drugs?” It is: “Does my current plan cover this exact product, for this diagnosis, under these clinical criteria, at this pharmacy, and at what out-of-pocket cost?” Get the answer in writing, give the correct policy to the prescriber, and treat a denial as a document with a specific reason—not as the end of the process.
Sources and further reading
- Centers for Medicare & Medicaid Services: Medicare GLP-1 Bridge information for Part D plans
- CMS: Medicare GLP-1 Bridge information for providers
- HealthCare.gov: Getting prescription medications
- HealthCare.gov: Internal appeals and external review
- CMS: Medicare Part D formulary and utilization-management exceptions
- U.S. Department of Labor: Filing a claim for health benefits
- FDA: Medications containing semaglutide marketed for diabetes or weight loss
Written and edited by: Denny Jaeyong Choi (JD), INSEAD MBA
Last updated: September 7, 2026
Medical information notice: This article provides general educational information and does not replace individualized medical advice, diagnosis, or treatment. Coverage rules change and your plan documents control. Discuss treatment decisions with a qualified clinician and verify benefits directly with your insurer.